
Anterior pelvic tilt, or an excessively arched lower spine, is frequently blamed as a major cause of lower back pain. Many people are told that their posture is out of alignment and that tight hip flexors or weak glutes are damaging their spine.
However, high-quality scientific research consistently shows that anterior pelvic tilt is a normal structural variation rather than a source of pain. Understanding what the evidence actually says is the first step toward moving past postural fear and restoring long-term spine health.
What Is Anterior Pelvic Tilt?
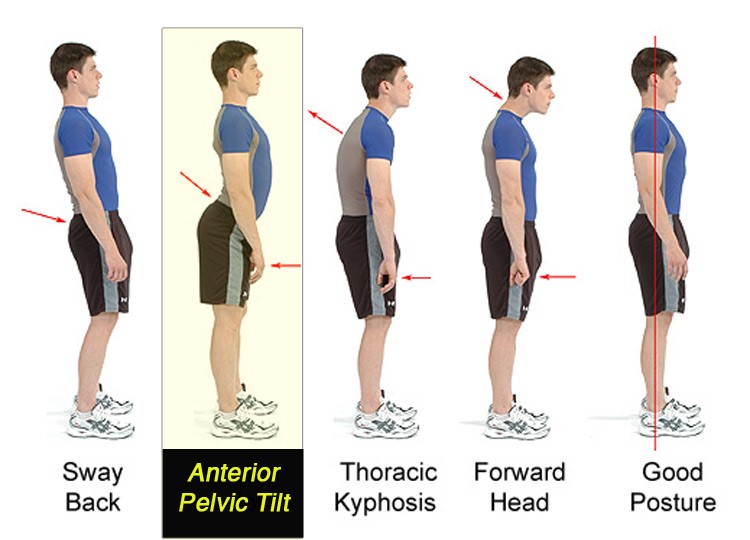
Anterior pelvic tilt refers to a posture where your pelvis is rotated forward, accompanied by an increased curve in your lower back (lumbar lordosis). Similar to how “text neck” is frequently linked to upper body posture, anterior pelvic tilt is commonly referred to as the lower body counterpart: lower crossed syndrome.
The traditional hypothesis claimed that tight back extensors and hip flexors combined with weak abdominals and gluteal muscles pull the pelvis forward. However, robust clinical studies have failed to validate this claim.
If a practitioner advises you to stretch your hip flexors and strengthen your core strictly to “fix” your anterior pelvic tilt for pain relief, they are relying on an outdated biomechanical model.
How Is Anterior Pelvic Tilt Evaluated?
Digital posture analysis applications like Posture Zone or PostureScreen evaluate body alignment against grid overlays. In a clinical setup, landmarking the ASIS (Anterior Superior Iliac Spine) and PSIS (Posterior Superior Iliac Spine) is standard procedure.
To locate the ASIS, place your hands at the top edge of your hip bone (iliac crest) and trace forward until you feel a distinct bony protrusion. Finding the PSIS usually requires assistance: locate the Dimples of Venus on the lower back and palpate downward to feel the underlying bony landmark.
If an imaginary line drawn between the ASIS and PSIS slants significantly forward, an anterior pelvic tilt is present. However, research proves this measurement tells us more about individual bone shape than underlying muscle imbalances.
Does Anterior Pelvic Tilt Cause Lower Back Pain? (What Science Says)
Numerous clinical studies demonstrate that pelvic tilt and lumbar lordosis do not correlate directly with lower back pain:
1. Hip Range of Motion vs. Alignment
Research evaluates no relationship between hip extension range of motion and standing pelvic tilt, standing lumbar lordosis, or abdominal muscle performance.
2. Lordosis in Back Pain Patients
Comparative studies show no significant difference in lumbar lordosis angles between individuals with and without low back pain.
3. Natural Anatomical Variation
Anatomical variations in pelvic structure significantly alter measurements, proving that tilt measurements reflect natural bone geometry rather than dynamic postural flaws.
4. Biomechanics of Lumbosacral Pain
Comprehensive assessments confirm no association between acute or chronic low back pain and lumbar lordosis angle, while broader mechanical reviews confirm that pelvic tilt and leg length discrepancies do not predict back pain incidence.
The Myth of Bad Posture & Temporary Passive Relief
Posture is largely a social construct. Scientific literature does not support the claim that structural alignment causes pain. Even asymptomatic individuals frequently show slipped discs or herniated discs on MRIs without experiencing symptoms.
Many people ask if lying flat on the floor with a yoga block or foam roller under their back gives good “decompression relief” for an arched spine. While passive positions can feel comfortable temporarily, relying on them indicates that your body’s load tolerance and movement capacity have not been addressed.
Temporary Comfort vs. Long-Term Adaptation
The better solution is to work with a professional to address any underlying issues you may have that could be causing your symptoms rather than modifying your pelvic tilt itself. In many cases, anterior pelvic tilt does improve as these issues are addressed. In other words, there is no need to directly change how your pelvis is sitting.
If you constantly need passive tools to seek decompression, something in your lumbopelvic mechanics or function is not working right. Passive relief manages symptoms temporarily, but active structured exercise builds lasting tolerance so discomfort does not occur in the first place.
Managing Load & Movement Technique in Compound Lifts
If you perform heavy compound exercises like squats and deadlifts while dealing with lower back discomfort or an extreme lumbar arch, subtle modifications can protect your spine while maintaining fitness progress:
- Check your technique: Executing heavy lifts in excessive lumbar extension under high exertion can lock in compensatory movement patterns and exacerbate spinal discomfort.
- Reduce or pause heavy compound loading: If lifting under heavy weights increases lower back irritation, temporarily reducing load or pausing barbell squats and deadlifts gives your back necessary recovery runway.
- Switch to single-joint machine exercises: Opting for machine-based or single-joint movements reduces technical complexity and spinal axial loading while allowing you to train target muscle groups safely.
- Reintroduce compound movements systematically: Compound lifts are superior for building strength only when executed correctly. Learning precise movement mechanics prevents dysfunction and restores confident loading.
- Seek professional assessment: DIY adjustments to complex lifts are often difficult to self-correct and often too reactive (i.e., fixing what looks wrong without evaluating the whole kinetic chain, aka frankenstein approach). Working with an evidence-based professional can help evaluate your movement technique, address specific force or motor control deficits, and rebuild proper execution under load.

Building Lumbopelvic Control: The Role of Clinical Pilates
While you do not need to change your posture to live free of pain, learning how to dynamically control and move through different pelvic positions is essential for resilience. This is where Clinical Pilates serves as a powerful active rehab tool.
Rather than trying to force a static “neutral spine,” apparatus-based Pilates (utilizing the Reformer, Trapeze Table, Cadillac, Wunda Chair, and Ladder Barrel) uses variable spring resistance to give feedback to your body. This helps you build:
- Dynamic motor control: Learning to tuck, tilt, articulate, and stabilize your pelvis under controlled, progressive resistance.
- Targeted trunk & hip strength: Loading the deep abdominal wall, gluteals, and lumbopelvic stabilizers through full ranges of motion.
- De-sensitization to movement: Helping your nervous system feel secure moving through positions that previously provoked discomfort, bridging the gap between basic rehab and heavy lifting.
How Active Chiropractic Care Resolves Back Pain
Virtually all clinical practice guidelines globally recommend progressive exercise rehabilitation as the first-line treatment for lower back pain. Seeking an evidence-based chiropractor in Singapore who focuses on active recovery provides better outcomes than relying on passive spinal adjustments or modalities alone.
Instead of fixing temporary structural “flaws,” active exercise rehabilitation empowers you with movement education, load management, dynamic movement systems like Pilates, and strength training. To explore clinical guidelines further, read our guide on lower back pain treatment options.
Key Takeaways
Keep these evidence-based facts in mind regarding pelvic tilt and back pain:
-
1
Anterior pelvic tilt does not cause back pain. Research shows no link between standing pelvic tilt, lumbar lordosis angle, and low back pain incidence. Anterior pelvic tilt is commonly observed in people with back pain but association is not causation.
-
2
Active exercise beats passive relief. Relying on passive decompression like yoga blocks offers only temporary relief. Structured exercise builds long-term movement tolerance and prevents discomfort from happening in the first place.
-
3
Clinical Pilates builds lumbopelvic control. Apparatus-based Pilates uses spring resistance to build dynamic trunk strength, motor control, and movement confidence without relying on passive fixes.
-
4
Modify compound lifts when in discomfort. If heavy squats or deadlifts provoke back pain, temporarily reduce load, refine technique, or swap to machine exercises.

